Beyond the Prescription Label: The Expanding Off-Label Role of Chloroquine in Modern American Medicine

Photo: U.S. Army 21TSC by Shaylee Borcsani, Public domain, via Wikimedia Commons
In American medicine, off-label prescribing is neither unusual nor inherently controversial. The FDA approves drugs for specific indications, but once a medication clears that regulatory threshold, licensed physicians are legally permitted to prescribe it for any condition they judge appropriate based on clinical evidence and professional judgment. By some estimates, off-label prescribing accounts for roughly one in five prescriptions written in the United States. Chloroquine, a drug that has been part of the American pharmacopeia since the 1940s, sits at an interesting intersection of this practice—simultaneously venerable and contentious, evidence-backed in some applications and speculative in others.
This feature examines the current landscape of chloroquine's off-label use in 2024, exploring where the evidence is strongest, where it remains thin, and what drives physicians to continue prescribing this drug for conditions that appear nowhere on its official label.
A Brief Regulatory Baseline
Chloroquine phosphate carries FDA approval for the treatment and prophylaxis of malaria caused by susceptible strains of Plasmodium species, and for the treatment of extraintestinal amebiasis. Its close structural analogue, hydroxychloroquine, holds additional approvals for lupus erythematosus and rheumatoid arthritis—approvals that chloroquine itself does not formally share in the United States, though it has historically been used for these conditions as well.
This regulatory distinction matters. When physicians prescribe chloroquine for lupus or rheumatoid arthritis—as some still do, particularly when hydroxychloroquine is unavailable or contraindicated—they are technically operating off-label, even though the clinical rationale is well-established and the two drugs share significant pharmacological overlap. The label, in other words, does not always reflect the full scope of a drug's evidence base.
Autoimmune Conditions: The Evidence-Adjacent Off-Label Zone
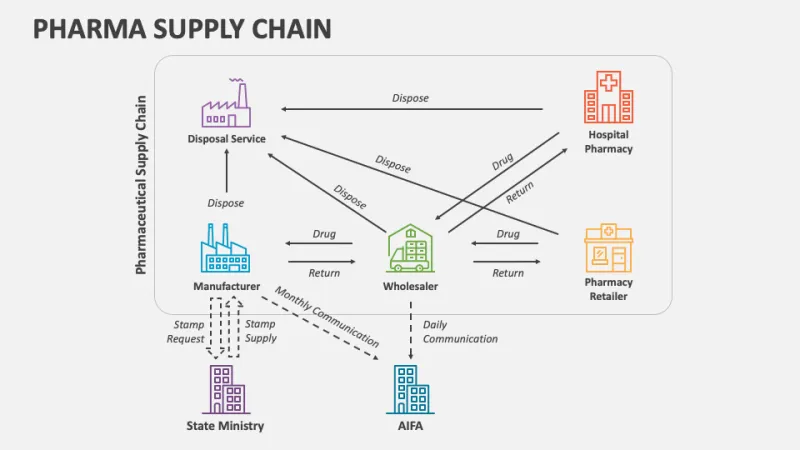
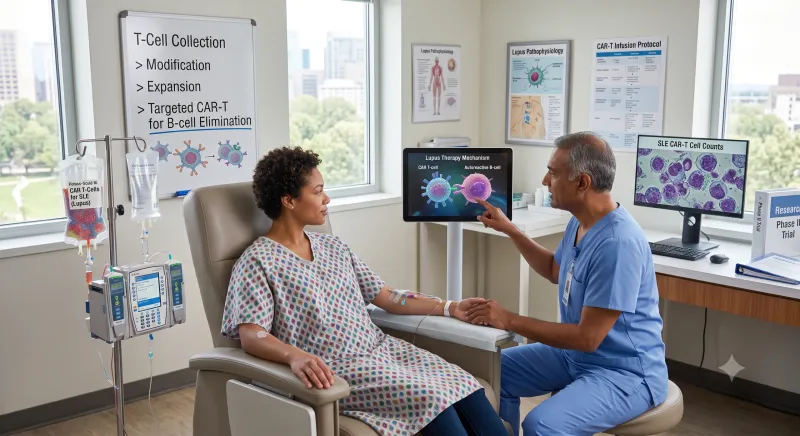
The most clinically defensible off-label territory for chloroquine in 2024 remains the autoimmune space. Physicians managing patients with systemic lupus erythematosus (SLE) have long relied on antimalarials as a cornerstone of long-term disease management. When hydroxychloroquine is unavailable—a situation that has occurred with troubling frequency due to supply chain disruptions in recent years—some rheumatologists turn to chloroquine as a substitute, drawing on decades of clinical experience with the drug class even when the specific agent differs from the approved one.
Similarly, chloroquine has been used in the management of discoid lupus, a chronic skin condition that can occur independently of systemic disease, and in certain presentations of Sjögren's syndrome. The mechanistic rationale is consistent across these applications: chloroquine's ability to modulate toll-like receptor signaling and interfere with antigen presentation makes it pharmacologically plausible as an immunomodulatory agent, even where head-to-head trial data specifically for chloroquine (rather than hydroxychloroquine) are limited.
Rheumatologists who prescribe chloroquine in this context are generally not operating in ignorance of the evidence gaps—they are making pragmatic clinical decisions informed by mechanism, drug class data, and patient need.
Dermatology: A Quieter But Persistent Use Case
Fewer patients and even fewer non-specialist physicians are aware that chloroquine has a meaningful history in dermatology. Beyond its use in cutaneous lupus, it has been employed in the management of porphyria cutanea tarda (PCT), a condition characterized by the accumulation of porphyrins in the liver and skin, leading to photosensitivity and blistering.
In PCT, chloroquine's utility stems from its ability to form complexes with porphyrins in hepatic lysosomes, facilitating their excretion. Low-dose chloroquine regimens for this indication have been described in the dermatological literature for decades, and while phlebotomy remains a first-line approach, chloroquine is considered an accepted alternative—particularly for patients in whom phlebotomy is not well tolerated. This is an area where off-label use is arguably as close to standard practice as it gets without formal FDA recognition.
Polymorphous light eruption, a common photosensitivity disorder, represents another dermatological application where chloroquine has been studied and used, though evidence here is more limited and hydroxychloroquine is typically preferred where available.
The COVID-19 Shadow: How a Controversy Reshaped Perceptions
No discussion of chloroquine's off-label landscape in 2024 can sidestep the COVID-19 episode. In early 2020, chloroquine and hydroxychloroquine surged into public consciousness when early—and ultimately poorly designed—studies suggested potential antiviral activity against SARS-CoV-2. The subsequent Emergency Use Authorization, the political amplification of these early signals, and the eventual withdrawal of that authorization following more rigorous trial data created a complex legacy.
For physicians who had used chloroquine responsibly for years in autoimmune and dermatological contexts, the COVID-19 controversy was a source of frustration. The drug's association with politicized science damaged its credibility in some quarters, even among clinicians who understood that the problem was not the drug itself but the premature extrapolation of weak data. In 2024, that shadow has not entirely lifted, but the medical community has largely moved past the acute controversy and returned to evaluating chloroquine on the merits of condition-specific evidence.
What the episode did underscore—constructively—is the importance of rigorous trial design before off-label use becomes widespread practice. The chloroquine-COVID story is now frequently cited in medical education as a cautionary example of how observational enthusiasm can outpace evidence.
Emerging Research Directions: What Physicians Are Watching
Beyond established off-label applications, a subset of researchers and clinicians are tracking chloroquine's potential in several emerging areas. Its autophagy-inhibiting properties have generated interest in oncology, where it has been studied as a potential adjunct to chemotherapy—the theory being that by blocking autophagy, chloroquine may prevent cancer cells from recycling damaged components to survive treatment stress. Multiple clinical trials have explored this in glioblastoma, pancreatic cancer, and other malignancies, with mixed but not discouraging results.
In the metabolic disease space, chloroquine's documented hypoglycemic effects have prompted investigation into its potential utility as an adjunct in type 2 diabetes management. Small studies have shown meaningful reductions in fasting glucose and HbA1c in patients treated with chloroquine, a finding that has not yet translated into mainstream clinical practice but remains an active area of inquiry.
Physicians following this research are not, for the most part, prescribing chloroquine for cancer or diabetes based on current evidence. But they are watching clinical trial data with genuine interest, which reflects the drug's ongoing scientific relevance.
Regulatory Considerations and the Physician's Calculus
For American physicians considering off-label chloroquine prescribing, the regulatory environment provides broad latitude but not unlimited freedom. The FDA does not prohibit off-label prescribing, but it does regulate how manufacturers may promote drugs for unapproved uses. Physicians bear the clinical and legal responsibility for off-label decisions, which means documentation of clinical rationale, informed patient consent, and alignment with the available evidence base are all essential.
In practice, the physicians most likely to prescribe chloroquine off-label in 2024 are specialists—rheumatologists, dermatologists, and some infectious disease specialists—who have direct familiarity with its pharmacology and risk profile. This is appropriate. Chloroquine is not a drug that benefits from casual prescribing; its interaction profile, ocular toxicity risks with long-term use, and narrow therapeutic considerations require a level of clinical familiarity that generalist prescribers may not always possess.
Conclusion: Evidence as the Enduring Standard
Chloroquine's persistence in American medicine beyond its labeled indications reflects a broader truth about pharmaceutical practice: drugs that are well-understood, widely available, and pharmacologically versatile tend to find clinical applications that their original approval processes never anticipated. In some of those applications, the evidence is strong. In others, it is preliminary. In a few, it remains genuinely uncertain.
The appropriate response to this reality is not reflexive skepticism of off-label use, nor uncritical enthusiasm for it. It is the same standard that should govern any prescribing decision: careful evaluation of available evidence, honest communication with patients about what is and is not known, and a commitment to updating clinical practice as data mature. Chloroquine, a drug that has survived decades of medical evolution, continues to earn its place on the prescription pad—where the evidence supports it.